


Hypospadias means that the opening where urine leaves the penis is on the underside rather than at the usual position at the tip. It develops before birth and is often recognised during the newborn examination. The first appointment is about understanding the particular anatomy and what it means for your child, rather than assuming every child needs the same operation.
More than the position of the opening
The foreskin may look like a hood, with more skin on the upper surface. Some children also have downward bending of the penis, called curvature or chordee. The opening can be near the tip or further along the underside. Its position alone does not describe the whole condition: curvature, skin, and the surrounding tissues also influence advice.
What might parents notice?
Urine may point downwards or spray, although many babies pass urine comfortably. Tell the clinician about a very narrow stream, straining, dribbling, or difficulty passing urine. Hypospadias itself does not usually cause pain. A child who cannot pass urine, becomes unwell, or has a markedly swollen, painful penis needs urgent medical assessment rather than waiting for a planned review.
The first examination
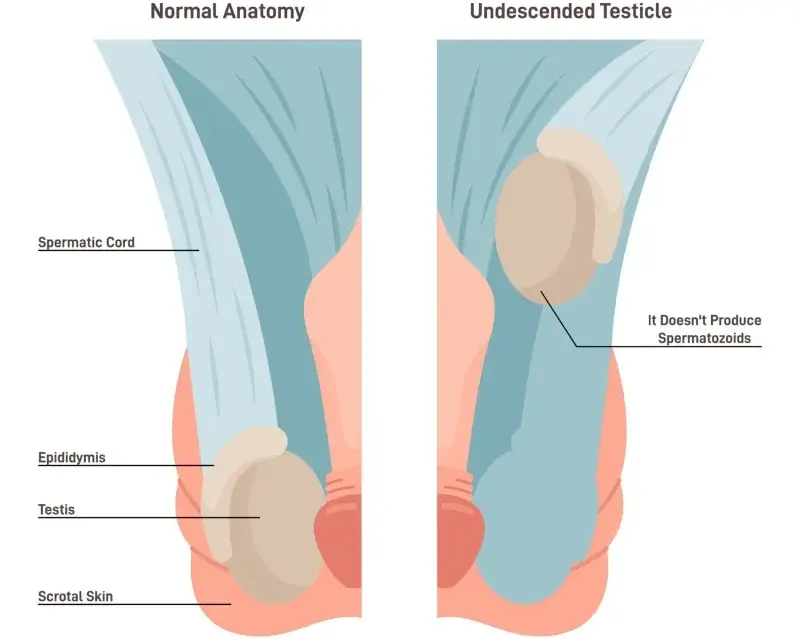
The clinician checks the opening, foreskin, curvature, and both testicles. Most isolated cases can be assessed by examination without routine scans. If hypospadias occurs with both testicles undescended or other genital differences, prompt specialist investigation is important. This may involve a wider team and blood tests; it does not mean that every baby with hypospadias has a hormone problem.
Keep the foreskin until advice is clear
Delay circumcision until a paediatric urology specialist has assessed your child. Foreskin tissue may be useful during reconstruction, depending on the operation. Use ordinary, gentle washing and nappy care. Do not stretch the opening, force the foreskin back, or apply products intended to alter the appearance. Ask the clinician to explain any unfamiliar wording in the newborn record.
Discussing observation and repair
Some very mild cases may be observed after discussion of urinary function, curvature, and future concerns. Hypospadias does not simply move to the usual position as the child grows. When repair is appropriate, the aims may include straightening the penis and improving urine direction. Surgery has limitations and possible complications, so a clear explanation of the benefits and follow-up belongs in the decision. Ask for the diagnosis and proposed next step in writing, so future appointments begin with the same information.
Planning your child's care
A consultation through DRHC with Dr. Mansour Masoumi, Specialist Urologist, can help clarify your child’s findings and arrange the appropriate paediatric specialist pathway. Bring previous reports and a list of your questions. The final treatment is chosen after individual assessment, with the child’s age, symptoms, and family circumstances taken into account.
Disclaimer
This article is educational and does not replace a medical consultation. Do not use it for self-diagnosis or self-treatment, or to start, stop or change your child’s medicines. Follow advice from the clinician responsible for your child’s care.

Learn more about our Editorial Process.
Topic: Urology Blogs



Leave a comment