


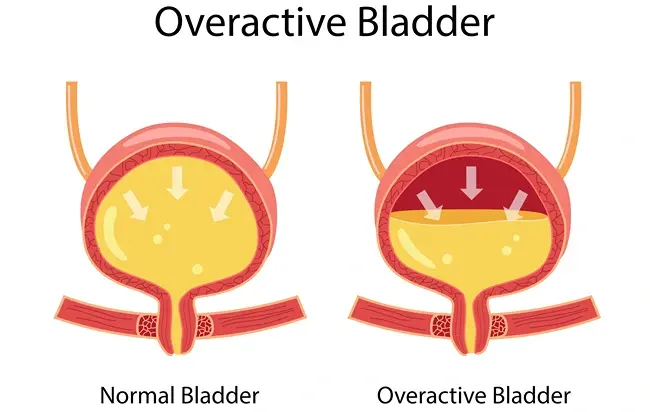
Bladder training is a structured way of improving control over urgency. It involves understanding your current pattern, learning how to respond to an urge, and gradually adjusting toilet visits where this is appropriate. It takes practice and review. The aim is not to endure pain or prove how long you can hold urine, but to make the bladder less dominant in everyday life.
Begin with a realistic baseline
A short bladder diary records drinks, toilet visits, urine volumes and leakage. This shows whether you are passing small amounts frequently, drinking large volumes at once or making many precautionary visits. Choose a goal linked to daily life, such as a calmer school run or fewer interruptions during a meeting. A clinician can help turn the diary into a plan that matches your starting point.
Responding to an urgent feeling
Your clinician may suggest pausing, breathing slowly and using a taught urgency-control technique before walking calmly to the toilet. Some people benefit from brief pelvic floor contractions once their technique has been assessed. Rushing and panic can make the situation harder to manage. The plan should be adapted if you have pain, a poorly relaxing pelvic floor or uncertainty about bladder emptying.
Changing intervals gradually
Training commonly lasts at least six weeks, with gradual adjustments rather than a sudden fixed schedule. Avoid repeated just-in-case trips when your clinician agrees that reducing them is suitable. Equally, do not ignore genuine fullness for prolonged periods. A setback during a busy day does not invalidate the programme. The diary can identify which parts need adjustment and whether additional treatment would be useful.
Drinks and bowel comfort
Try reducing caffeine if it seems relevant, including caffeinated tea, coffee, energy drinks and cola. Spread drinks through the day instead of taking most of them in one sitting. Fluid needs vary with heat, exercise and other health conditions, so avoid rigid advice taken from someone else’s plan. Address constipation as part of care, since straining and bowel discomfort can complicate pelvic symptoms.
Fit treatment around your life
Plan access to toilets while practising, and use protective products if they help you stay active. Ask about work routines, travel, and sleep separately because they may need different solutions. Review progress with your clinician; medicines can be considered alongside training when needed. New burning, fever, blood or difficulty passing urine calls for assessment, rather than simply trying harder with the exercises.
Arrange an individual review
A consultation through DRHC with Dr. Mansour Masoumi, Specialist Urologist, can help put these options into the context of your symptoms, health, and priorities. Bring previous reports and a list of medicines, including non-prescription products. The final treatment is chosen after individual assessment and discussion of the options appropriate for you.
Disclaimer
This article is for education only and does not replace medical advice. It is not intended for self-diagnosis or self-treatment. Do not start, stop, or change treatment on the basis of this information; discuss your own care with a qualified clinician.

Learn more about our Editorial Process.
Topic: Urology Blogs



Leave a comment